Starting October 1, Radiology Partners will further “share the efficiency gains” from their Mosaic platform, which includes AI drafts for specific exams as well as a voice recognition application layer (i.e., PowerScribe replacement capable of natural language dictation). This summary chart has been making the rounds across the internet:
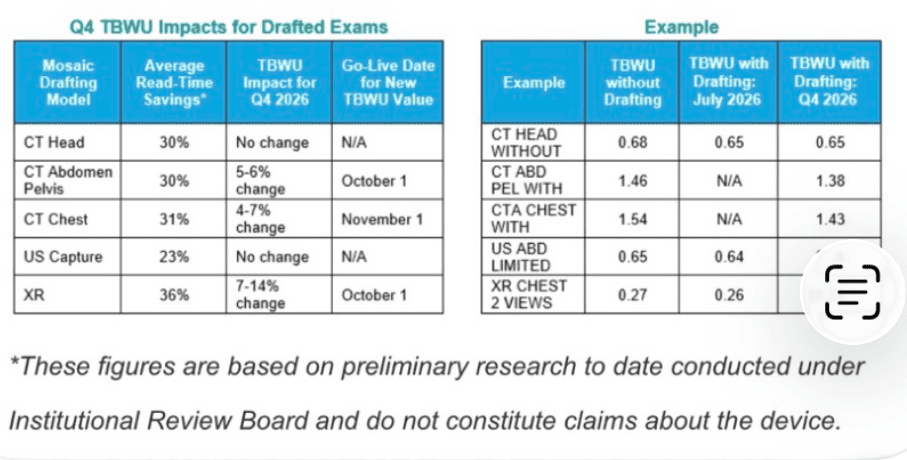
In an email to their radiologists, they reported reading time savings on the order of 30% and initial work unit reductions ranging from 4–14%.
For those joining us without reading the first three entries in the series:
RP moved to a time-based work unit (TBWU) earlier this year, stating they were internally adjusting RVUs based on average read times. They also said they’d be adjusting those numbers on a quarterly basis to account for efficiency gains from using RP tools. As in, when Mosaic decreases average read time, RP decreases the associated TBWU by some fraction of that time savings, thereby “sharing” the efficiency gain.
They suggest this only applies to AI drafts, which one does not have to use at this point, and not to any efficiency gain from the broader Mosaic platform as a whole. Both the software and the drafts have very mixed reviews, including some that are very positive (I’ve used neither). It is also very much worth pointing out that many RP radiologists work for local RP groups that do not pay per click and may not be meaningfully impacted by changes to how their RVU meter grows over the course of the day (as opposed to RP’s Matrix teleradiology division and especially its independent contractors, where it presumably is a big deal).
Average Gains, Individual Cuts
The baseline we use for how much AI drafting itself helps is critical.
While some commenters and users doubt the reported efficiency gain, RP has no reason to share its data, so it’s a matter of trust. The party doing the measuring is the same one profiting from the measurement. But even if the gain on the whole was accurate across their entire book of business, that does not mean you as an individual are that much faster or that the average efficiency gain applies to the work you do (especially if you were already efficient). However, the cut does!
While drafting can undoubtedly save some time and some mental effort, how does an AI draft compare to high-quality findings-only dictation, generative impressions, AI proofreading and follow-up management with regard just to speed? Most radiologists are still using PowerScribe 360. I have no doubt we would see substantial gains as a field for moving to a better dictation product. How AI drafting impacts sensitivity, specificity, overall quality, job satisfaction, skill, etc are all of course important open questions.
Regardless, you get the generic cut, even if you personally don’t see the same benefit when using the drafting product.
The Golden Age
If productivity goes up before reimbursement goes down, there is a temporary golden age of profitability. Who gets to enjoy that?
Medicare and the commercial payors are not currently paying less for a chest CT because Mosaic helped write the report. The TBWU is an internal accounting unit. So when the internal value of the radiologist’s work goes down while external reimbursement stays the same, that difference has to go somewhere. Looks like RP is going to be taking more of that, as promised.
The payor won’t feel bad for the doctors. When reimbursement eventually goes down, a physician-owned practice that enjoyed the golden age may simply return to something like baseline: the cut takes back temporary gains the partners already captured. RP radiologists won’t get that symmetry. They will have already absorbed the efficiency cut internally, and they’ll eat the external cut on top of it. One maintains a balance; the other adds insult to injury.
None of this is an argument against AI making radiologists more efficient. I would very much like better tools that make the job easier and faster. The interesting question is who captures the value created by that efficiency. Technology can make the pie bigger without answering how the bigger pie gets divided.
Rapid Cuts
That RP is moving so quickly in reducing work credit suggests a couple of possibilities. The obvious one, based on behavior so far, is that they think the vast majority of their radiologists won’t quit or do anything about the frog boiling. Nonetheless, a few here and a few there can add up to a real problem over time. RP presumably believes the labor consequences of these adjustments are manageable, or it would not make them.
A related possibility is that they have modeled increased attrition in this context, but feel that the current and coming efficiency gains will absorb those changes. Perhaps better for the squeaky wheels to leave now than keep them around polluting the vibes. By making multiple small adjustments quickly, they’re running a breeding experiment, selecting for those radiologists who are willing to play in the system and getting rid of those who are unwilling or uncomfortable to work faster and rely on AI drafting in its current and coming iterations.
The fact that they have exempted breast imaging from this so far suggests at least some component of that. One could argue that screeners are already fast, and so efficiency gains would be relatively small. But the fact that AI drafting has not been used in this setting, I would surmise, has more to do with the desire to not run off breast imagers in a hot job market (and jeopardize the mammo cash cow and its contract-anchoring effect) rather than a lack of technical capability. A large fraction of breast imagers cannot be replaced with remote contractors, surge pricing incentives, or any of the other typical tools that a practice can use to get a long list back in shape. IR and, to an extent, breast imaging are simply a different beast.
Vertical Integration
Doing it in-house, like RP has done with Mosaic after purchasing Cognita, and as Harrison.ai is attempting to do by starting Frontier Radiology, is the vertical integration playbook. An internally developed model deployed within a radiology practice is arguably an extension of practicing medicine and just helping the radiologist do the work (at least for now). It’s felt to be an easier regulatory pathway than making and then selling the software as a service. Selling software also requires interested and willing customers.
The fact that RP just agreed to spend a reported $715 million buying international teleradiology firm Everlight suggests a desire to get its tendrils into a global market to anchor and develop its software across a larger, more diverse practice. One could make a metastasis analogy, but I won’t.
The economic incentive for all the AI stuff is to either do AI drafting in ever-increasing volumes under the current payment paradigm or get paid a smaller amount for truly autonomous work. I think medicolegally and also probably just from a raw reimbursement perspective, what RP is doing is the logical first approach. Presumably the goal is to use all the rads as a meat bridge to continue their pivot to basically being a technology company with machine work either being rubber-stamped in increasingly large amounts (+/- eventually some of the negatives being fully AI-read when the climate, data, and reimbursement support that approach). The more contracts and rads they own, the more they can do this.
Another benefit of being early and vertically integrated is that it enables them the option of not just trying to sell their software to others but also, if it feels right, to try to pull up the rope ladder behind them by petitioning the government to bring down the regulatory hammer, making it harder for people selling radiology AI as a service to find customers and get their products approved. Perhaps it should come as no surprise that RP’s subsidiary Cognita this month was awarded a $1.29 million grant from the FDA to use a team of LLMs to assess/evaluate AI-generated reports. Of course that’s not intrinsically anticompetitive, but it’s undeniably a structural advantage should they pursue that strategic possibility.
This Won’t Be Unique
This is the part where we should point out that Radiology Partners is a company of humans trying to make money and acting in its own best interest, as we should expect any company to do. Certainly, the rank-and-file radiologists, and even many of those in leadership, have little to no control over this policy or its justification and marketing.
It is in the best interest of every employer of radiologists—whether those owned and operated by private equity, large health systems, or anywhere else—to pay as little as possible for acceptable-quality work. That is the economic incentive, and therefore that is also the trend we should expect to see.
In the private equity model, RP is first in line here because of their size and their technology purchases. The other big employers in this space (other than potentially RadNet) do not have internal AI tools to this degree or the vertical integration. Most are and will be using a variety of third-party tools.
Being early isn’t always a durable competitive advantage. Everyone who can do this will do this. Other companies are still working on radiology tools, and we will be seeing more products including AI drafting out in the wild. The whole field will have to contend with how to incorporate AI in a way that balances patient care, maintaining physician skill, and striking a balance of tool cost and profit sharing.
Radiologists are not going to turn the clock back on changes like this, and without regulation, we are unlikely to change the style of AI development and deployment in the current climate. Making radiologists read faster, spinning up the hamster wheel to blistering speeds while using the humans as a liability sink, is by far the easiest and most straightforward way for this to play out. This is somewhat true in physician-owned private practices (who want to capture efficiency gains for partners and need to compete in the labor market, often with weaker payor contracts and without the benefit of technical-service revenues) and especially true for all employers (who logically want shorter turnaround times and higher margins).
RP is likely not a particularly unique company other than being the biggest radiology rollup and single largest employer of radiologists in the country. That, again, is why it deserves scrutiny. What they do impacts the field and is thus of interest to radiologists around the world.
Radiologists have the choice to play in that system or to work for groups/companies that handle these interesting times differently.
Ultimately, this is the economic logic AI introduces into radiology. RP is simply large, vertically integrated, and early enough that we can watch that logic unfold in real time.